Ivermectin or Molnupiravir

Citation: Ajayi AAL. Drugs Shown to Inhibit SARS-CoV-2 in COVID-19 Disease: Comparative Basic and Clinical Pharmacology of Molnupiravir and Ivermectin. Austin J Pharmacol Ther. 2021; 9(5).1149.Austin J Pharmacol Ther – Volume 9 Issue 5 – 2021ISSN: 2373-6208 | www.austinpublishinggroup.com Ajayi. © All rights are reservedAustin Journal of Pharmacology and TherapeuticsOpen AccessAbstractThe pharmacology of anti-SARS-CoV-2 drugs, Molnupiravir (M) and repurposed Ivermectin (IV) were compared. The IC50 for the inhibition of viral replication were 0.3μM for M and 2.8μM for IV. Both drugs have good oral absorption, with M achieving peak plasma concentrations by 2 hours and IV by 5 hours. The plasma half life were 7 hours for M and 81-91 hours for IV. M inhibits viral replication inducing viral mutagenesis in RdRp, causing viral error catastrophe and viral extinction. IV affects viral cell entry, nuclear transport and inhibits replication via RdRp. IV has additional effect to suppress cytokine production through STAT-3 inhibition. M is a more potent antiviral drug and IV has a longer residence in the body. Their effects on RdRp and cytokine inhibition are potentially complimentary for anti-COVID-19 activity. Both IV and M should be compared in randomized controlled clinical trials, and the possibility of their combination for anti-SARS-CoV-2 antiviral actions, explored further. Keywords: COVID-19; Antiviral therapeutics; Molnupiravir; Ivermectin; CombinationIntroductionThe COVID-19 pandemic caused by SARS-CoV-2, has affected more than 120 million people and resulted in nearly 3 million deaths worldwide. Although vaccine roll out is mitigating the community transmission and enabling a reopening of global economy piecemeal, there are still many nations where vaccines are not yet widely available, and new viral variants are emerging. There is a gradual shift in focus, to antiviral drugs, both for possible adjunctive chemoprophylaxis, as well as for active treatment of patients with new SARS-CoV-2 infections, or post -vaccination breakthrough COVID-19 cases. There have been purposive efforts, to develop novel and specific antiviral drugs for SARS-CoV-2, and to repurpose existing FDA -approved drugs to treat COVID-19. Molnupiravir is the most advanced of the novel antiviral drugs undergoing clinical development and trials, whilst Ivermectin is the most studied “repurposed” medication globally, in randomized clinical trials, retrospective studies and meta-analyses. This mini- review examines and compares their basic and clinical pharmacology and the possible utility of their combination, in treating COVID-19 and future corona virus diseases.Molnupiravir and Ivermectin Anti-SARS-CoV-2 Mechanisms, Pharmacokinetics and PharmacodynamicsMolnupiravir (EIDD2801/MK-4482) is a pro-drug of the novel active antiviral nucleoside analogue β-d-N4-hydroxycytidine (NHC, EIDD1931) [1]. It’s a broad spectrum antiviral agent against SARS-CoV-2, SARS-CoV,seasonal or pandemic influenza and MERS corona virus [1]. The basic and clinical pharmacological properties are shown on Table 1. Ivermectin is an FDA-approved, WHO essential drug used as broad spectrum antiparasitic, antibiotic and Ajayi AAL*Department of Medicine, Division of Hypertension and Clinical Pharmacology, Baylor College of Medicine, USA*Corresponding author: Ajayi AAL, Department of Medicine, Division of Hypertension and Clinical Pharmacology, Baylor College of Medicine, Houston TX 77030, USAReceived: July 10, 2021; Accepted: August 03, 2021; Published: August 10, 2021Mini ReviewDrugs Shown to Inhibit SARS-CoV-2 in COVID-19 Disease: Comparative Basic and Clinical Pharmacology of Molnupiravir and Ivermectinwhich has demonstrated broad spectrum antiviral activity against RNA viruses, including HIV, Zika, MERS corona virus. It is being repurposed as a therapeutic agent for COVID-19, after in vitro studies in Vero/hSLAM cells, showed that it caused a 5000-fold inhibition of SARS-CoV-2, (99.98% at 48 hours) with an IC50 of 2.8μM [2]. The corresponding in vitro IC50 of molnupiravir for SARS-CoV-2 is 0.3μM in Vero cells and 0.08μM in Calu-3 Cells [3]. The IC50 of Molnupiravir shows it to be a more potent anti-SARS-CoV-2 agent, compared to Ivermectin in vitro. Both molnupiravir and ivermectin are well absorbed after oral dosing, the Tmax of molnupiravir being 1-1.75 hours , with a half life of 7 hours, 1 whilst the Tmax of ivermectin is 4-6 hours, and a very long half life of 81-91 hours [4]. Ivermectin, being lipophilic has a large volume of distribution (Vd) and the ability to accumulate in the lungs [5], the major target organ of COVID-19. Molnupiravir is given twice daily, and doses of 400 and 800 mg showed viral clearance by RT-PCR [1]. By contrast, the dosing regimen of ivermectin in randomized clinical trials with RCT-PCR SARS-CoV-2 clearance, varied from 12mg daily [6], to 12mg twice a week [7]. The anti-SARS-CoV-2 actions, both of molnupiravir and ivermectin, are dose and concentration dependent [1,7]. Pharmacodynamically, the mechanisms of anti-SARS-CoV-2 action, both of molnupiravir and ivermectin are overlapping and complimentary (Table 1). Molnupiravir active metabolite (NHC-5’ Triphosphate), acts as a competitive alternative substrate for the viral RNA dependent RNA polymerase (RdRp), causing viral mutagenesis or transition mutations, which leads to viral error catastrophe and extinction of replication [8]. There is some concern about the safety of NHC -nucleoside triphosphate, which is also mutagenic to mammalian cells [9]. Ivermectin (Table 1) exhibits multifarious actions, ranging from binding to SARS-CoV-2 spike protein S, reducing cell entry via human ACE2 receptors, inhibition of the

Austin J Pharmacol Ther 9(5): id1149 (2021) – Page – 02Ajayi AALAustin Publishing GroupSubmit your Manuscript | www.austinpublishinggroup.comnuclear transport of viral proteins, which prevents interference with replication, to binding to RdRP, reducing the activity of the viral transcription -replication complex [10]. Ivermectin has additional effects on Signal Transduction Activation of Transcription (STAT-3) and inhibition of cytokine production and inflammation, which has not yet been shown for molnupiravir.As most but not all double blind studies, and meta-analyses, have shown benefits of ivermectin in COVID19 including 56% mortality reduction [11], and given the complimentary pharmacokinetics and pharmacodynamics of the drugs, direct head -to -head comparison of molnupiravir and ivermectin, in blinded randomized clinical trials are needed. A combination of molnupiravir with Ivermectin putatively, may be at least additive or synergistic in effects on RdRP or cytokine release. This should be further investigated in anti-SARS-CoV-2 antiviral combination therapy.References1.Painter WP, Holman W, Bush JA, Almazedi F, Malik H, Eraut CJEN, et al. Human safety, tolerability, and pharmacokinetics of Molnupiravir, A novel broad- spectrum oral antiviral agent with activity against SARS-CoV-2. Antimicrob Angents Chemother. 2021; 65: e02428-e02520.2.Caly L, Druce JD, Catton MG, Jans DA, Wagstaff KM. The FDA -approved MolnupiravirIvermectinChemical structure/NameRiboNucleoside analogue. Pro-drug of β-d-N4 Hydroxycytidine (NHC), EIDD 280122,23 dihydroavermectin B1a + B1b (80:20) mixturePharmacokineticsAbsorption and F Distribution (Vd) Metabolism Excretion routes T ½ (hours) Mean Residence Time (hours) Tmax (hours)Daily dosesSARS-CoV2 IC50RapidProdrug > EIDD1931 (plasma esterases) > active 5’ATP EIDD (tissue kinases).7 hours?1-1.75 hours20.3μM (Vero cells) 0.08μM (Calu cells)414.6 nM (Syrian Hamster)Good 9-12L/KgHepatic CYP3A4 mainly, 3A5, 2C9, 2D6Fecal >99%81-91 hours84 hours5 hours12.5-2-8 μM (E, RdRP cell associated virus genes)Vero-h/SLABPharmacodynamicsAntiviral mechanisms•Cell viral entry-hACE2 receptor. •Nuclear transport -importin α/β1•RNA dependent, RNA polymerase (RdRp)*Viral mutagenesisDose/Concentration-anti SARS-CoV-2 response??Competitive alternative substrate for SARS-CoV-2 RdRP viral genome >excessive mutations > viral error catastrophe > viral extinction.YesDose -Dependent Viral RNA clearance in human phase 2A study.Binds to active sites of spike protein S. Inhibits human cell entrance of virus via h-ACE2.Binds Importin α to prevent link with β1 and nuclear transport of viral and host proteins.Binds to and inhibits viral RdRp replication and transcription complex with -9.7Kcal/mol energyNoSignificant dose and concentration dependent virucidal response seen in humans.Effects on Cytokines & interleukins (IL)?Inhibits Janus Kinase (JAK) Signal transduction Activator of Transcription (STAT-3) and IL-6/10Clinical Trials and Real World EfficacyRT-PCR CasesPhase 2A shows dose dependent high anti-SARS-CoV-2 efficacy in COVID-19.Mixed outcomes. Meta-analyses show clinical and laboratory benefits and mortality reduction. Adverse effects and Drug-Drug InteractionsNo Serious Adverse effects compared to placebo.No Serious Adverse Effects. Dizziness Table 1: Comparison of Anti-SARS-CoV-2 pharmacology of Molnupiravir and Ivermectin.drug ivermectin inhibits the replication of SARS-CoV-2 in vitro. Antiviral Res. 2020.3.Sheahan TP, Sims AC, Zhou S, Graham RL, Pruijsssers AJ, Agostini ML et al. An orally bioavailable broad-spectrum antiviral inhibits SARS-CoV-2 in human airway epithelial cell cultures and multiple corona viruses in mice. Sci Trans Med. 2020; 12: eabb5883.4.Munoz J, Ballester MR, Antonijoan RM, Gich I, Rodriguez M, Colli E, et al. Safety and pharmacokinetic profile of fixed dose ivermectin with an innovative 18 mg tablet in healthy adult volunteers. PLoS Negl Trop Dis. 2018; 12: e0006020.5.Duthaler U, Suenderhauf C, Karlsson MO, Hussner J, Schwabedissen HMZ, Krahenbull S, et al. Population pharmacokinetics of oral ivermectin in venous plasma and dried blood spots in healthy volunteers. Br J Clin Pharmacol. 2019; 85: 626-633.6.Elgazzar A, Hany B, Yousef SA, Hafez M, Moussa H. Efficacy and safety of ivermectin for treatment and prophylaxis of COVID-19 pandemic in Egypt. 2020.7.Babalola OE, Bode CO, Ajayi AA, Alakaloko FM, Akase IE, Otrofanowei E, et al. Ivermectin shows clinical benefits in mild to moderate COVID-19: A randomized controlled, double blind, dose response study in Lagos. QJM An international Journal of Medicine. 2021.8.Wahl A, Gralinski LE, Johnson CE, Yao W, Kavarova M, Dinnon 3rd KH, et al. SARS-CoV-2 is effectively treated and prevented by EIDD-2801. Nature. 2021; 591: 451-457.
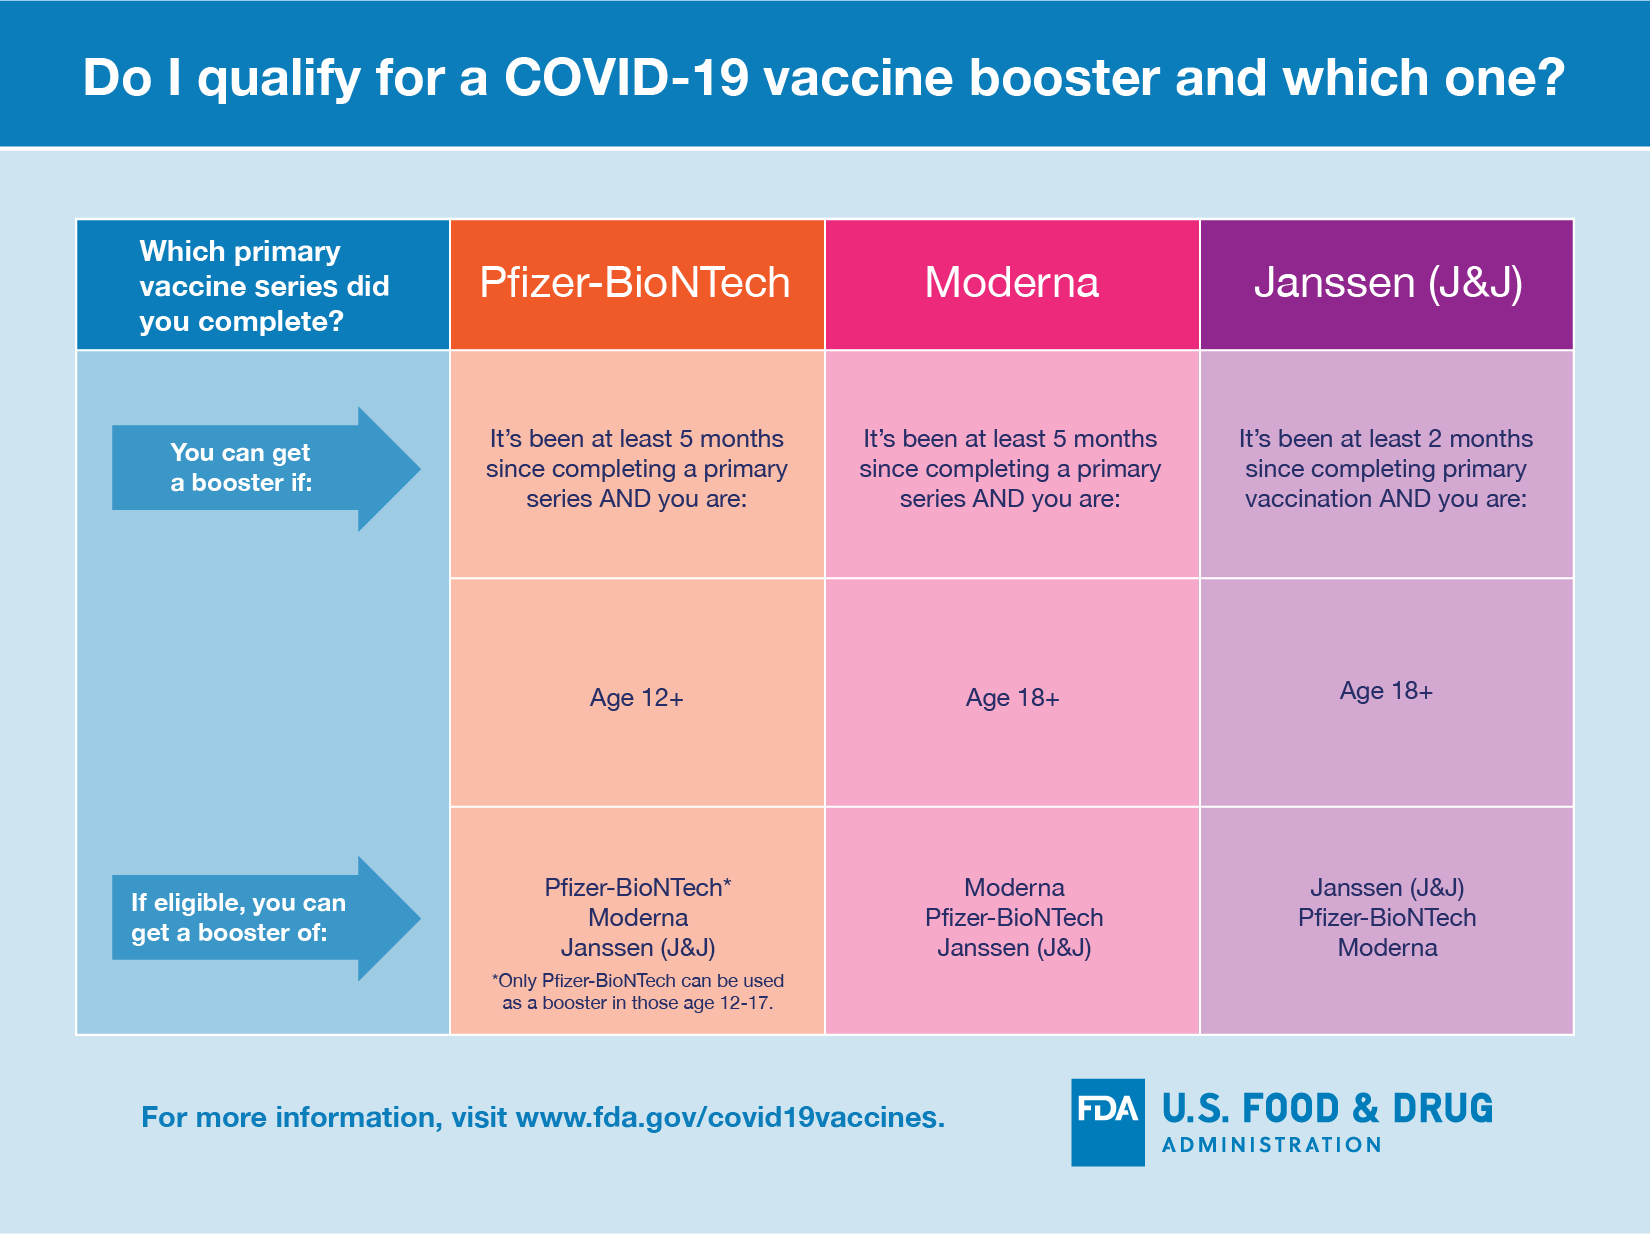
FDA shortens interval for Moderna booster dose

Today, the U.S. Food and Drug Administration amended the emergency use authorization (EUA) for the Moderna COVID-19 Vaccine to shorten the time between the completion of a primary series of the vaccine and a booster dose to at least five months for individuals 18 years of age and older.

“The country is in the middle of a wave of the highly contagious omicron variant, which spreads more rapidly than the original SARS-CoV-2 virus and other variants that have emerged,” said Peter Marks, M.D., Ph.D., director of the FDA’s Center for Biologics Evaluation and Research. “Vaccination is our best defense against COVID-19, including the circulating variants, and shortening the length of time between completion of a primary series and a booster dose may help reduce waning immunity. Today’s action also brings consistency in the timing for administration of a booster dose among the available mRNA vaccines. We encourage everyone to get vaccinated—it’s never too late to get your COVID-19 vaccine or booster.”

The most commonly reported side effects by individuals who received a booster dose of the Moderna COVID-19 Vaccine after completion of a two-dose primary series were pain, redness and swelling at the injection site, as well as fatigue, headache, muscle or joint pain and chills. The fact sheets for recipients and caregivers and for healthcare providers include information about the potential side effects, as well as the risks of myocarditis and pericarditis.

The amendment to the EUA was granted to ModernaTx Inc.

Moderna Booster Infographic 01072021

Omicron pushes U.S. COVID hospitalizations toward record high

(Reuters) – COVID-19 hospitalizations in the United States are poised to hit a new high as early as Friday, according to a Reuters tally, surpassing the record set in January of last year as the highly contagious Omicron variant fuels a surge in the number of cases. Hospitalizations have increased steadily since late December as Omicron quickly overtook Delta as the dominant strain of the coronavirus in the United States, although experts say Omicron will likely prove less deadly than prior variants. While deemed less severe, health officials have nevertheless warned that the sheer number of infections caused by Omicron could strain hospital systems, some of which have already shown signs of distress, partly due to staffing shortages. “I don’t believe we’ve seen the peak yet here in the United States,” Centers for Disease Control and Prevention (CDC) Director Rochelle Walensky told NBC News’ “Today” program on Friday, as schools and businesses also struggle with rising caseloads.

The United States reported 662,000 new COVID cases on Thursday, the fourth highest daily U.S. total ever recorded and just three days after a record of nearly 1 million cases was reported, according to the Reuters tally.

The seven-day average for new cases set a record for a 10th day in a row at 597,000 new infections, while COVID hospitalizations reached nearly 123,000 and appeared poised to top the record of over 132,000 set last year in the coming days. Deaths, an indicator that lags behind hospitalizations, remain fairly steady at 1,400 a day, according to the tally, well below last year’s record numbers, although they typically lag behind case numbers and hospitalizations. “We are still seeing those numbers rising,” Walensky said, noting that while cases outpaced hospitalizations and deaths, rising hospitalizations were primarily among the unvaccinated.

Delaware, Illinois, Maryland, Pennsylvania, Ohio, Vermont and Washington, D.C., all reported record levels of hospitalized COVID patients in recent days, according to the Reuters analysis.

Hospitalization data, however, does not differentiate between cases of people admitted to hospitals for COVID-19 and so-called incidental positives: patients who were admitted and treated for issues other than COVID-19 and contracted the virus while in the hospital and are counted in coronavirus hospitalization numbers. Incidental infections have occurred throughout the pandemic but might be significantly higher now due to the staggering pace of Omicron’s spread – a phenomenon that has prompted state health departments to consider altering their disclosures. Starting next week, Massachusetts hospitals will report whether admissions are primary or incidental to COVID-19, Kathleen Conti, a spokesperson for the state’s department of health, said. Rising cases have forced hospital systems in nearly half of U.S. states to postpone elective surgeries. While many school systems have vowed to continue in-person instruction, some have faced ad hoc closures as cases rise. Chicago Public Schools, the third-largest U.S. education district, were closed for a third day on Friday amid a teacher walkout over COVID-19 protections. U.S. and other officials have said schools can be safely opened, especially amid widely available vaccines and boosters, and the CDC on Thursday issued new guidelines for schools on isolation policies. While the United States is fighting a surge right now, the country will have to face the long-term impacts, Walensky said. “We are definitely looking at a time ahead of us where COVID … will be an endemic virus,” the CDC director told NBC. Officials continue to press vaccinations as the best protection against COVID, although federal mandates requiring them have become politically contentious. The U.S. Food and Drug Administration on Friday shortened the interval between the primary series of the Moderna MRNA.O COVID-19 vaccine and a booster dose by a month for people aged 18 or above to at least five months. The regulatory decision comes days after the agency made a similar move and cut the interval for booster shot eligibility to five months from six for the Pfizer PFE.N and BioNTech BNTX.O COVID-19 vaccine. The Pfizer booster shot has also been authorized for use in children aged 12 to 15. Overwhelmed by Omicron surge, U.S. hospitals delay surgeries

US nonfarm payrolls up by 199,000 in December

  • The US added 199,000 payrolls in December, missing the average forecast of 450,000 new jobs.
  • The unemployment rate slid to 3.9% from 4.2%, beating economist estimates.
  • The report suggests the Omicron wave is having a significant effect on the US hiring recovery.

Hiring faltered again in December as the Omicron variant fueled yet another wave of coronavirus cases and economic restrictions. The US added 199,000 nonfarm payrolls last month, the Bureau of Labor Statistics announced Friday. Economists surveyed by Bloomberg held a median forecast of 450,000 added jobs. The print reveals hiring slowed in the final weeks of 2021 as coronavirus case counts swung higher and fueled new concerns for the still-incomplete recovery. November job growth was revised to 249,000 jobs from 210,000, according to the report. The latest count marks the worst month of job creation since December 2020, when the country shed 306,000 payrolls. The unemployment rate slid to 3.9% from 4.2%, BLS said. That landed below the median forecast of 4.1%. The report offers a gloomy look at how the labor market was performing as it entered the new year. The slump in job creation suggests the recovery isn’t as resilient to Omicron as some hoped. The unemployment rate’s steady decline still signals the labor market could return to pre-pandemic health by the end of 2022. To be sure, the data only covers the recovery through mid-December. Daily virus case counts went parabolic later in the month as the more contagious variant proliferated amid holiday travel. Infections continued to surge higher in January and haven’t yet shown signs of a consistent easing. While virus deaths are a fraction of the counts seen during last year’s winter wave, the variant’s contagion is still placing new pressure on businesses and Americans eyeing a return to the workplace. The number of jobless Americans dropped by 483,000 to roughly 6.3 million, according to the report. On the payrolls front, the economy has about 3.6 million jobs to add before returning to its pre-pandemic total. Labor force participation held flat at 61.9 in December, still 1.5% lower than the level seen before the pandemic. The measure, which tracks Americans working and in the process of finding work, has been among the slowest to recover. Federal Reserve Chair Jerome Powell raised concerns around the sluggish rebound in December. Economists “certainly thought” the ending of enhanced unemployment benefits and increase in vaccinations would lift participation, he said. There’s been “some improvement,” but “we don’t have a strong labor force participation recovery yet,” he added in the December 15 press conference. The average hourly wage rose by 19 cents, or 0.6%, in December to $31.31. That beat the median estimate of a 0.4% gain. Wages increased at a faster pace than usual throughout 2021 as the labor shortage gripped the recovery. Businesses quickly boosted pay to attract workers, with low-paying sectors exhibiting some of the biggest raises. Data published earlier in the week suggests that overwhelming demand for workers lingered well into the fourth quarter. US job openings totaled 10.6 million in November, according to Job Openings and Labor Turnover Survey, or JOLTS, data published Tuesday. While that’s down from the prior month’s 11 million, it’s still historically high and signals weak job uptake throughout the economy. A record 4.5 million workers quit their jobs in November, hinting the so-called Great Resignation also charged forward. The accommodation, food services, health care, and transportation sectors saw the most quits, suggesting the pandemic’s spread played a major role in prompting people to walk out. The Friday report offers economists the most detailed look yet at where jobs were created and where they were erased in the last month of 2021. Leisure and hospitality businesses continued to drive much of the payroll recovery. The sector added 53,000 nonfarm payrolls through December, the most of any industry. Still, employment at such businesses remains 1.2 million payrolls below the pre-crisis level, and the sector was likely hit hard by the virus surge seen later in December. Professional and business services followed with a gain of 43,000 payrolls. Retailers lost 2,100 jobs through the month as Omicron powered new concerns around in-person shopping. Sporting goods and hobby stores saw the largest decline of 12,500 payrolls, according to the report. Government jobs dropped by 12,000 mostly due to declines in state and local government employment.

Omicron spike in most vaccinated German state heralds nationwide surge

BERLIN, Jan 7 (Reuters) – The northern German maritime state of Bremen has the country’s highest COVID-19 vaccination rate by far, but it has become the hardest-hit by the rapid spread of the Omicron variant, reporting the highest infection rate of any region in Germany. Experts say that the spike in Bremen could herald where Germany as a whole is heading in the coming days. The seven-day infection rate in Bremen stood at 800 cases per 100,000 residents on Thursday, the highest in Germany and more than double the national rate of 303, according to the Robert Koch Institute (RKI) for infectious diseases. “I assume that Bremen is just a little further ahead than other federal states,” said Hajo Zeeb of the Leibniz Institute for Prevention Research and Epidemiology in Bremen. He said he expected many of Germany’s federal states to report infection rates similar to Bremen in the coming days. Germany’s leaders are set to discuss how to respond to the Omicron variant later on Friday, with measures including shortening COVID-19 self-isolation periods over fears that critical services could grind to a halt as case numbers spike. Bremen’s location near the Netherlands and Denmark, where Omicron has already become the dominant variant, could be one reason for the higher infection rate in the state, Zeeb said. Omicron now accounts for more than 85% of coronavirus infections in Bremen, well above the national figure of around 44%, according to data from the RKI on Thursday. Also, the city’s success in inoculating most of its residents early last year could be another reason. “You have possibly now more of a vaccine gap than others who were a bit later (with the vaccination),” he said. Studies have shown that protection against Omicron wanes over the course of several months  and increases again following a booster shot. Close to 84% of the population in Bremen, the smallest of Germany’s 16 federal states with fewer than 700,000 people, are double-vaccinated, compared with a national figure of around 72%. Some 44% have received a booster shot, compared with 42% nationally. Bremen is also a somewhat more accurate representation of the actual figures in Germany because coronavirus testing there did not slow during the holiday season as it did in many other regions, Zeeb added. Last week, German Health Minister Karl Lauterbach said the number of new cases had been under-reported and the actual incidence rate of infections was about two or three times higher than the officially reported figure. The state’s government on Thursday introduced further restrictions to curb infections, including requiring a negative rapid test or proof of a booster shot to enter restaurants or cultural events, in addition to proving double-vaccination. Despite the record infection rate in Bremen, the state’s hospitals were not as burdened as they were in the first three waves of the pandemic as patients infected with the new variant were coming in with milder symptoms, said Lukas Fuhrmann, spokesperson for Bremen’s health senate. Doctors say the situation in hospitals could however soon worsen and that non-intensive care units were already overburdened with patients with milder lung symptoms. The city of Bremen’s seven-day hospitalisation incidence was 13.6 cases per 100,000 people on Thursday, three times the national incidence of around 3. “The situation is certainly a nightmare,” said Felix Diekmann, the medical director at St. Joseph-Stift hospital in Bremen. Although the situation is still manageable, the city might have to send COVID-19 patients to other states if it runs out of its intensive care beds, he said.

NY reports highest single day covid deaths

  • According to state data, 130 New Yorkers died due to COVID-19 on Wednesday, with 62 alone coming from New York City
  • As of Thursday, over 11,000 people are hospitalized, the highest number since the spring 2020 peak when the state was utilizing field hospitals
  • But daily deaths remain much lower than during that period, when up to 816 were dying across the state every day  
  • Governor Kathy Hochul said in a statement that New Yorkers should continue to wear a mask, get vaccinated and wash your hands
  • New York City, with a positivity rate of nearly 33 percent, now accounts for over half of the hospitalizations across the state 
  • Hospital officials in the Big Apple still say that things are nowhere near as bad as they were at the dawn of the pandemic 

New York State and New York City saw some startling COVID-19 numbers Thursday, with the most deaths in one day since vaccinations begin, but both death and hospitalizations remain down from their 2020 peak. According to state data, 130 New Yorkers died due to COVID-19 on Wednesday, with 62 alone coming from New York City. That’s the most since mass vaccination started, but still well below the record 816 who died in one day during the first peak in April 2020.

As of Thursday, over 11,000 people are hospitalized, the highest number since the spring 2020 peak when the state was utilizing field hospitals.      

‘Wearing a mask, washing your hands, getting your vaccine, your second dose, your booster – we are not defenseless and these are things you can do to keep yourself and your loved ones safe and healthy,’ Governor Kathy Hochul said in a statement. ‘As we make our way through the winter surge, it is important to keep the wellbeing of others in mind,’ Hochul added. ‘Be mindful of how your actions impact others so we can keep our communities open and thriving.’

The state has lost just over 49,000 people to COVID-19 since the beginning of the pandemic.   The state also announced 84,202 new cases, just below the state’s single-day record of 85,476 on New Year’s Day.  Led by the spread of the Omicron variant, the state’s positivity rate on tests is at 22.3 percent.    The CDC estimates that omicron, the first NY case of which was confirmed on Dec. 2, now accounts for upwards of 99 percent of current COVID-19 cases in the region  New York City, with a positivity rate of nearly 33 percent, now accounts for over half of the hospitalizations across the state. Hospital officials in the Big Apple still say that things are nowhere near as bad as they were at the dawn of the pandemic. ‘We’re not even halfway to what we were in April 2020,’ Dr. David Battinelli, the physician-in-chief for Northwell Health, New York state’s largest hospital system, told NBC4.  Experts add that patients aren’t as sick as they were getting earlier during the first surge.  For example, while 666 patients are currently in ICU beds – the highest total since February 2021 – that’s still five-fold less than where they were at in April of 2020.   The WHO said Thursday that a record 9.5 million COVID-19 cases were tallied over the last week as the omicron variant of the coronavirus swept the planet, a 71 percent increase from the previous 7-day period that the U.N. health agency likened to a ‘tsunami.’  That said, the number of weekly recorded deaths declined. NN: they are selling that the Omicron mutation is not that deadely myth. NOT TRUE!  Somebody is showup at the emergency rooms. Record numbers are hosipitalized. Do not be fooled this is serious and getting worse by the day.

N.Korea graduated from Scud-B to htpersonic missiles

North Korea said Thursday it has conducted a second hypersonic missile test, a sophisticated technology it is pursuing as a top priority for its arsenal. North Korea started working in the late 1970s on a version of the Soviet Scud-B missile with a range of around 300 kilometres carrying out its first test in 1984. Between 1987 and 1992, it developed longer-range missiles, including the Taepodong-1 (2,500 km) and Taepodong-2 (6,700 km).The Taepodong-1 missile was test-fired over Japan in 1998 but the following year, Pyongyang declared a moratorium on such tests as ties with the United States improved. However, in 2005 the moratorium ended as North Korea blamed the “hostile” policy of US President George W. Bush’s administration and carried out its first nuclear test on October 9, 2006. In May 2009 the North Korean regime conducted a second underground nuclear test, several times more powerful than the first. Kim Jong-Un succeeded his father Kim Jong Il who died in December 2011 and oversaw a third nuclear test in 2013.  North Korea then conducted a fourth underground nuclear test in January 2016 which Pyongyang claimed was hydrogen bomb.  In March, Kim claimed North Korea had successfully miniaturised a thermonuclear warhead. In April, it test-fired a submarine-launched ballistic missile. On August 3, it launched, for the first time, a ballistic missile directly into Japanese-controlled waters. Later that month, it successfully test-fired another SLBM. Between February and May 2017, Pyongyang launched a series of ballistic missiles that fell into the Sea of Japan also known as the East Sea in Korea.  North Korea claimed it was meant to hit US bases in Japan. In May, Pyongyang said it had tested the “newly developed mid/long-range strategic ballistic rocket, Hwasong-12”. It flies 700 kilometres before landing in the Sea of Japan. Two months later, North Korea announced it had successfully tested on July 4 an inter-continental ballistic missile capable of reaching Alaska – a gift for the “American bastards” announced on US Independence Day. Kim’s regime also conducted a second successful ICBM test on in July. Former president Donald Trump threatened Pyongyang with “fire and fury” over its missile programme. However, North Korea conducted its sixth and largest nuclear test on September 3, 2017. Monitoring groups estimated a yield of 250 kilotons, which is 16 times the size of the 15-kiloton US bomb that destroyed Hiroshima in 1945. Within days, the United Nations adopted an eighth series of sanctions as North Korea fired an intermediate-range missile over Japan.  Just over a month later, Washington declared North Korea a “state sponsor of terrorism”, a day before adding to pressure on the isolated state with fresh sanctions. Pyongyang launched a new Hwasong-15 ICBM which it claimed could deliver a “super-large heavy warhead” anywhere on the US mainland.  Analysts agree the rocket is capable of reaching the United States but voice scepticism that Pyongyang has mastered the advanced technology needed to allow the rocket to survive re-entry into the Earth’s atmosphere. In his New Year speech in 2018, Kim said the development of North Korea’s nuclear force has been completed but catalysed by the Winter Olympics in South Korea, a rapid diplomatic thaw begins in February. In 2018, Pyongyang said nuclear blasts and ICBM launches will cease immediately and the atomic test site at Punggye-ri will be dismantled to “transparently guarantee” the end of testing. However, After the Hanoi summit in February 2019, negotiations between the United States and North Korea were deadlocked. There was fresh tensions in 2021 with North Korea carrying out a number of high-profile weapons tests, including a claimed submarine-launched ballistic missile, a long-range cruise missile, a train-launched weapon, and what it says is a hypersonic gliding missile. In its first major weapons test of 2022, North Korea said it has carried out a second hypersonic missile test, with a warhead capable of gliding as well as lateral movement during flight. The test on Wednesday “reconfirmed the flight control and stability of the missile in the active-flight stage and assessed the performance of the new lateral movement technique applied to the detached hypersonic gliding warhead”, KCNA said. The launch also verified the “fuel ampoule system under winter weather conditions”, it added. Seoul and Tokyo had detected the launch of a suspected ballistic missile from North Korea that fell in the sea east of the Korean peninsula. The United States condemned the launch and urged Pyongyang to sit down for talks. NN: the world is well past the talking stage. Kim Yon Num Chucks has achieved the impossible for such a poor isolated country. He is truly a evil genus. Ruthless, calculating and close to unstoppable. He is holding the entire country of S.Korea hostage to thousands of missiles aimed at them.

Global coronavirus infections surpass 300M

Global COVID-19 cases topped 300 million on Thursday, according to the Center for Systems Science and Engineering at Johns Hopkins University.

The United States reported 58,449,898 cases and 833,957 deaths, both the highest counts around the world, accounting for more than 19 percent of the global cases and more than 15 percent of the global deaths.

The global caseload reached the grim milestone of 100 million on Jan. 26, 2021 and rose to 200 million on Aug. 4. Maria van Kerkhove, technical lead for the World Health Organization’s Health Emergencies Program, said Thursday that current COVID-19 vaccines do work against all variants that are circulating and are highly effective against preventing severe diseases and death. “I think that’s really important for the public to know … when it is your turn, get vaccinated because it’s really critical,” she said. NN: I am increasing my warnings. The numbers are a blur. They are playing lost of games  with the stats. My conclusion is the Omicron variant may be just as deadly.  My sniff is it takes longer to get into the lungs but but BUT eventually it gets their. SO you need to go into FULL isolation. If you must go out say to get a booster shot mask up with a proper silicon rubber mask with a cartage ULPA filter. Take you immune booster vitamins especially D3. with the proper combination of other vitamins and minerals. AND MOST IMPORTANT OF ALL GET A BOOSTER SHOT. If your last vaccine is more then 4  months old get the jab. Protocols vary among jurisdictions. But it is fairly consistent. I f you jab is 4 to 6 months old its time to get another. We are out of test kits but we have everything else in stock. I f you need any supplies call us. Its not about money Call Jim at 866-924-0607 if you can’t afford supplies we will supply them to you at no charge. Do not be shy….. Go to our online store and see what we have. If you can’t afford supplies call Jim and we will send you what you need AT NO CHARGE WHATS SO EVER.

Critical Covid19 Supplies click here

Gas gap in Europe drives U.S. LNG exports to record high

https://youtu.be/XdQz-jmU44g

HOUSTON/LONDON (Reuters) – Sky-high European demand drove U.S. liquefied natural gas (LNG) exports to a record in December, Refinitiv data showed, with winter supply worries set to sustain orders for the fuel.About half of the record U.S. LNG volumes shipped last month went to Europe, up from 37% earlier in 2021, data from Refinitiv and the U.S. Energy Information Administration showed. The gains reflected soaring demand for the home heating and industrial fuel that pushed prices in Europe and Asia to record highs. The United States has ample and cheap supplies as its shale oil and gas boom in the last two decades led to domestic production that has exceeded U.S. demand by about 10%. Vessel tracking data showed about 7.15 million tonnes of LNG were shipped last month on 106 vessels, up 16% compared to 6.14 million tonnes on 89 vessels the same month a year ago. That topped the previous record of 6.51 million tonnes set in May. Dutch gas prices, the European benchmark, have cooled since late December removing their premium to Asia. On Wednesday, the Japan Korea Marker (JKM) price for Asia spot gas was $34.19 per million British thermal units, a premium of about $4 to Europe. Two LNG cargoes originally destined for Europe have been re-routed this month, people familiar with the matter said, with one heading to Asia. That is a reversal to late last year when at least 10 cargoes heading for Asia were re-routed to Europe attracted by the price differential. “LNG diversions from Asia are a useful stop-gap measure but are not a sustainable substitute for stable pipeline supplies,” Wei Xiong, senior analyst at consultancy Rystad Energy, said. LNG demand in Asia may jump in January, halting further diversions to Europe, she added. “Prices are volatile right now,” said Reid I’Anson, senior commodity analyst at data provider Kpler.While LNG prices being higher in Asia than in Europe lowers the likelihood of a new record for U.S. exports to Europe, flows could shift again if temperatures tumble there, I’Anson said. Ports in Britain, the Netherlands and Belgium have around 30 LNG tankers scheduled for delivery this month, with at least 13 arriving from the United States. While the United States has plentiful natural gas, its processing and chilling capacity is limited. Gas flowing to U.S. LNG export plants in December hit a record 12.2 billion cubic feet per day, about the maximum processing capacity. There were no LNG processing plants approved in the United States last year, while nearly a dozen plants proposed in past years are still awaiting financial commitments. Spending on new LNG projects fell in recent years as trade tensions between the United States and China rose and more recently as gas prices fell during the COVID-19 pandemic.

Oil extends rally on Kazakhstan unrest and Libyan outages

  • Russia moves paratroopers into Kazakhstan to quell uprising
  • Libyan oil output down to 729,000 bpd, NOC says
  • Market shrugs off U.S. fuel stock surge, OPEC+ output hike

NEW YORK, Jan 6 (Reuters) – Oil prices rose about 2% on Thursday, extending their new year’s rally, on escalating unrest in OPEC+ oil producer Kazakhstan and supply outages in Libya.